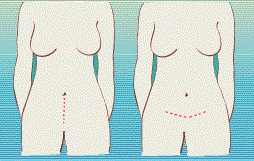
A Cesarean section, usually just called a C-section, lets your doctor deliver your baby safely and quickly when a vaginal birth isn’t the safer option. During the procedure, your doctor makes a cut in your lower belly and into your uterus, then delivers your baby through that opening. Most people start feeling more like themselves again after about four to six weeks, though everyone heals at their own pace.
There are several reasons a C-section might be the right call. Your baby could be positioned wrong, your baby’s head might be too large to fit through your pelvis comfortably, your contractions might not be doing enough to move labor along, or you may have had a C-section with an earlier pregnancy.
Watch this short video for a visual walkthrough of what happens during a C-section.
More about C-sections today
Cesarean delivery has been the most common surgery performed in the United States for decades now. As of 2024, about 32.4 percent of babies, nearly one in three, are born by C-section, according to the CDC. That’s actually higher than it was back in the 1980s, when the rate first crossed 20 percent and people were already calling it overused.
Some critics still argue C-sections happen more often than they need to, pointing to the extra recovery time and surgical risk involved. But the reasoning is simpler than the debate makes it sound. A C-section gets recommended when your care team believes a vaginal delivery would put you or your baby at more risk than the surgery would. Most people stay awake for the procedure, usually with an epidural or spinal block rather than general anesthesia, and your partner can typically stay right by your side. The delivery itself usually takes five to ten minutes from the first incision, then another 30 to 45 minutes to close everything back up. Because you’re recovering from actual surgery, you’ll likely feel more sore in the days after than you would following a vaginal birth, so give yourself permission to take it slow for a few weeks.
How do you know if a C-section is really necessary
Here’s a look at the most common reasons doctors recommend one.
A previous C-section
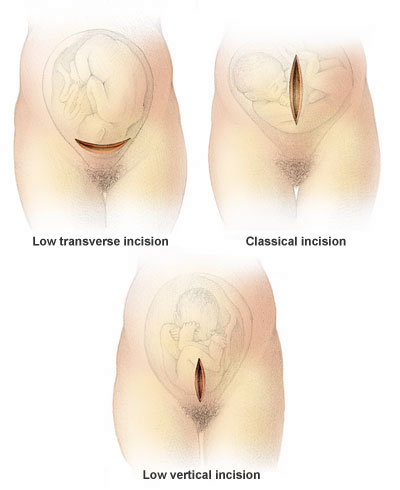
This is still the single biggest reason for a repeat C-section. Doctors used to worry that a uterus with a prior C-section scar would rupture during a later vaginal labor, but that risk turns out to be quite small, especially with a low horizontal incision. Because of that, plenty of doctors now support attempting a vaginal birth after cesarean, or VBAC, when both mother and baby are healthy.
Dystocia
This is the medical term for when your baby’s head is too big to fit through your pelvis, or when labor just isn’t progressing the way it should. Before jumping to surgery, it’s worth trying the relaxation techniques from your childbirth classes and experimenting with different positions. Some doctors will also try oxytocin to help contractions along before considering a C-section.
Breech position
This means your baby’s feet or bottom are positioned to come out first instead of head down. Plenty of breech babies turn on their own before delivery, and your provider may also try to turn the baby manually. While some providers will still deliver a breech baby vaginally, most breech births end up being C-sections.
Fetal distress
This can happen if your baby isn’t getting enough oxygen. Signs include a change in your baby’s heart rate or meconium in the amniotic fluid, which happens when your baby has a bowel movement in the womb and turns the fluid green, yellow or brown instead of clear. Your care team might monitor your baby more closely or take a blood sample to figure out whether a C-section is needed.
Health conditions
Premature labor, high blood pressure, diabetes, or other health issues can sometimes make a vaginal delivery too risky to attempt.
Why C-section rates have climbed over the decades
- Medical technology has come a long way, letting doctors catch problems early and deliver by C-section babies who might not have survived a generation ago.
- Malpractice concerns play a role too. Lawsuits against obstetricians have grown over the years, and the legal risk tied to a difficult vaginal delivery can push some doctors toward a C-section sooner than may be medically necessary.
- There’s also a bit of a snowball effect. Once someone has had a C-section, some doctors default to another one for future deliveries even when a vaginal birth is possible, despite VBAC being safer and more widely accepted than it used to be.
What is a VBAC
A VBAC, or vaginal birth after cesarean, means attempting labor after a previous C-section, which can end in either a vaginal delivery or another C-section. Current research shows somewhere between 60 and 80 percent of people who attempt a trial of labor after cesarean go on to deliver vaginally, and the risk of uterine rupture with a single prior low transverse incision is under 1 percent.
What makes someone a good candidate for VBAC
- Neither you nor your baby has any major health complications.
- Your care team can closely monitor you and your baby throughout labor.
- Your previous C-section used a horizontal, or low transverse, incision on the uterus rather than a vertical one.
Doctors generally steer away from VBAC if you’ve had a classical vertical incision, a prior uterine rupture, or certain other uterine surgeries, since those raise the risk of rupture during labor.
Why some people choose VBAC
- Lower risk. A vaginal delivery usually comes with fewer complications for both you and your baby than another surgery would.
- Faster recovery. Without a surgical incision to heal from, you’ll likely feel back on your feet sooner.
- More active role. Many people simply want to experience labor and feel more involved in the birth itself.
Questions worth asking your doctor about a C-section
- Are you planning to deliver by C-section, and if so, why? Are there other options?
- My last baby was born by C-section. Would you support me trying a vaginal birth this time?
- If labor stalls, would you try other approaches, like medication, before moving to a C-section?
- If the fetal monitor shows signs of distress, will you confirm that reading another way before deciding on a C-section?
- Would the type of incision used affect my ability to try a vaginal birth with a future pregnancy?
- Can my partner stay with me during the C-section and hold the baby right after birth?
- Can my baby stay in the room with me afterward?
- How long should I expect to stay in the hospital?
- What kind of discomfort or physical limits should I expect afterward?
Taking care of yourself once you’re home
- A firm ridge may form along your incision. That’s normal, and it’ll soften as the area heals.
- A heating pad on low, or a warm damp towel, can help ease soreness around the incision.
- Showering is fine. Just wash gently over the incision with a mild, unscented soap.
- Skip douching unless your doctor specifically tells you to.
- Ease back into your normal routine as your body allows, rather than rushing it.
- Most doctors recommend waiting at least two weeks before driving, though your own timeline depends on how you’re healing and whether you’re still on pain medication that affects your reflexes. Check with your doctor before getting behind the wheel.
- Ask your doctor when it’s safe to have sex again. Most people get the okay around their six week postpartum checkup, but it really depends on how you’re recovering.
- When you’re nursing or feeding your baby, resting them on a pillow over your incision can make things more comfortable.
When to call your doctor
Reach out to your doctor if you’re soaking through more than one pad an hour, if your bleeding turns bright red again after tapering off, if vaginal discharge or bleeding is still going strong after six weeks, if an urgent need to urinate isn’t easing up, or if you notice pain, redness or warmth down one leg, which can be a sign of a blood clot.